

Most tongue ulcers and sore spots heal on their own within a week or two. A small number don’t, and that is when it is worth paying attention.
This guide explains the early signs of tongue cancer, who is more at risk, how it is diagnosed and treated, and when to see a dentist or doctor. It also answers 10 questions people often ask when they are worried about a spot on their tongue.
Quick answer
The most common early sign of tongue cancer is an ulcer, sore, lump, or red or white patch on the tongue that does not heal within 3 weeks. Early tongue cancer is often painless. Other symptoms include mouth pain that won’t go away, difficulty swallowing or speaking, numbness, ear pain on one side and a lump in the neck.
These symptoms are much more often caused by something harmless. Even so, anything that lasts longer than 3 weeks should be checked by a GP or dentist. Tongue cancer is usually treated with surgery, sometimes followed by radiotherapy or chemoradiation, and the outlook is much better when it is found early.
What is tongue cancer?
Tongue cancer is cancer that starts in the cells of the tongue. Most tongue cancers begin in squamous cells, the thin, flat cells that cover the tongue’s surface. Doctors call this squamous cell carcinoma.
Cancer develops when changes (mutations) build up in a cell’s DNA. These changes switch off the normal controls on cell growth, so the cell divides when it shouldn’t and forms a tumour. Tobacco and heavy drinking are thought to raise the risk by damaging the DNA of cells lining the mouth and throat. Usually several changes are needed before a cancer forms.
Front of the tongue vs base of the tongue
Doctors split tongue cancer into two types, because they have different causes, symptoms and treatment.
|
Oral tongue |
Base of tongue |
|
|
Where it is |
The front two-thirds, the part you can stick out |
The back third, towards the throat |
|
What it is classed as |
Oral cavity (mouth) cancer |
Oropharyngeal (throat) cancer |
|
Main known risk factors |
Tobacco, alcohol, betel quid and areca nut |
Human papillomavirus (HPV), tobacco, alcohol |
|
Typical first sign |
An ulcer, patch or lump you can see or feel, often on the side of the tongue |
A sore throat, trouble swallowing, ear pain on one side or a painless lump in the neck |
Because the base of the tongue is hard to see, cancer there is more often found later, sometimes only when a lump appears in the neck.
How common is tongue cancer?
Tongue cancer is relatively uncommon. In the United States, the National Cancer Institute’s SEER programme estimates about 20,420 new cases in 2026, around 1% of all new cancers. The median age at diagnosis is 65, and it is more common in men than in women.
It can affect younger people too. Researchers have reported more oral tongue cancer in younger adults who have never smoked, and the reasons are not yet clear.
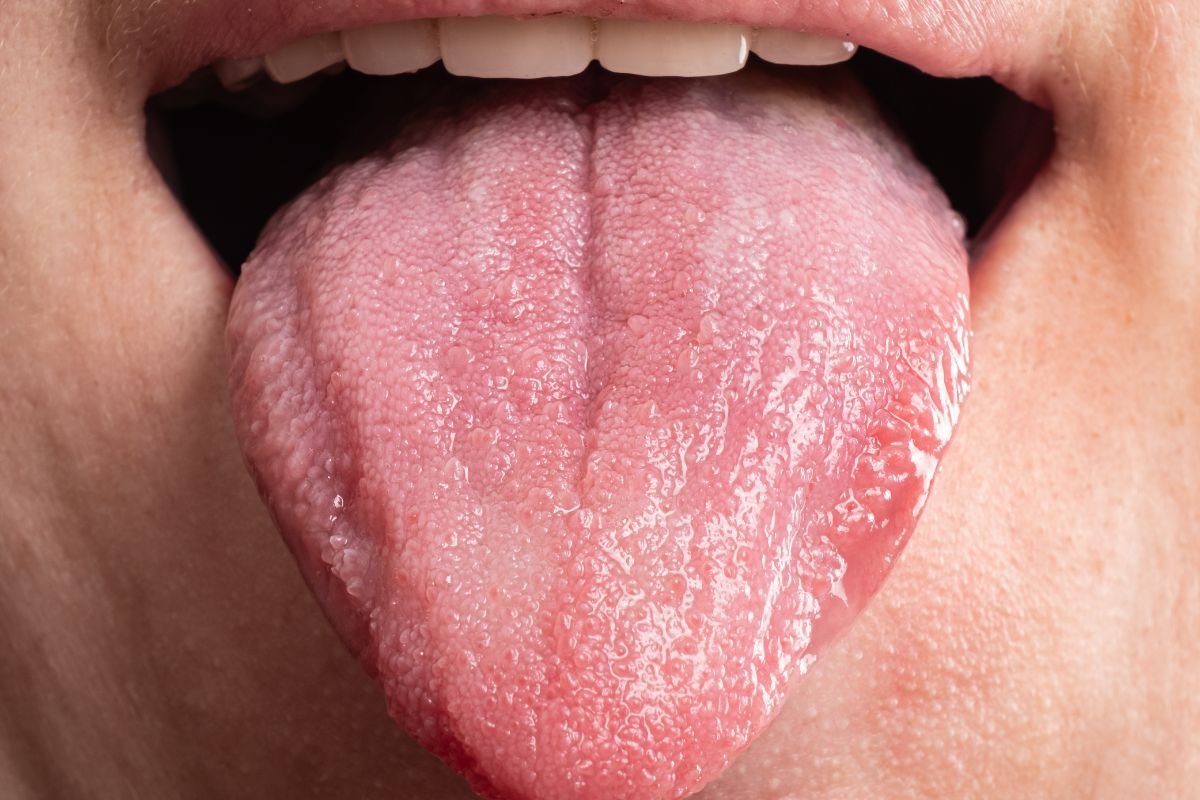
Early signs and symptoms of tongue cancer
Symptoms depend on where the cancer is and how far it has grown. See a GP or dentist if you notice any of the following:
- An ulcer or sore that won’t heal. This is the most common early sign. It is often on the side of the tongue and may or may not hurt.
- A red or white patch. A white patch is called leukoplakia and a red patch is called erythroplakia. Both can be harmless, but some contain abnormal cells that can turn into cancer.
- A lump or thickened area on or under the tongue.
- Pain that doesn’t go away, sometimes spreading to the ear on the same side.
- Difficulty swallowing, chewing or moving your tongue.
- Changes to your speech or a hoarse voice.
- Numbness in the tongue or mouth.
- Bleeding from the tongue with no obvious cause.
- A lump in the neck, which can mean cancer has reached the lymph nodes.
- Weight loss without trying.
Symptoms of base of tongue cancer
Cancer at the back of the tongue is less likely to be seen in a mirror. Signs include a sore throat that lasts, a feeling that something is stuck in your throat, pain in one ear, a change in your voice and a painless lump in the neck.
Is tongue cancer painful?
Not always. Early tongue cancer is often painless, which is one reason people wait. In one small study of early-stage tongue cancers, about half of the patients (13 of 24) reported pain. A sore that doesn’t hurt still needs checking if it lasts.
Ordinary mouth ulcer or something to check?
Only a clinical examination, and often a biopsy, can tell the difference. This table shows the general patterns.
|
Usually an ordinary ulcer |
Get it checked |
|
|
How long it lasts |
Clears up within a week or two |
Lasts more than 3 weeks |
|
Cause |
Often obvious, such as a bite, sharp tooth or hot food |
No clear cause, or keeps coming back in the same place |
|
How it changes |
Gets smaller each day |
Stays the same, grows or changes colour |
|
How it feels |
Tender, with soft edges |
May be painless, raised, firm or bleed easily |
When to see a dentist or doctor about a tongue symptom
See a GP or dentist if you have a mouth ulcer lasting more than 3 weeks, a lump, a red or white patch, mouth pain that won’t go away, or difficulty swallowing or speaking. This follows the NHS advice on mouth cancer symptoms, which also stresses that these symptoms are common and usually caused by other conditions.
Go sooner if the area is growing quickly, bleeding, numb, or if you also have a lump in your neck. Don’t wait just because it doesn’t hurt.
A dentist is well placed to examine your tongue. If you can’t get a routine appointment, our guide to emergency walk-in dentists and NHS urgent dental care explains other ways to be seen.
Before your appointment:
- Note the date you first noticed the problem.
- Take a clear photo every few days so you can show any change.
- List other symptoms, such as ear pain or trouble swallowing.
- Tell the dentist or doctor if you smoke, chew tobacco or betel nut, or drink alcohol.
How to check your own mouth: in good light, use a mirror to look at the top and both sides of your tongue. Lift it to see underneath. Look inside your cheeks and lips, and gently feel along both sides of your neck for lumps.
What causes tongue cancer? Risk factors
The exact cause of most tongue cancers isn’t known, but several factors raise the risk:
- Tobacco in any form. Cigarettes, cigars, pipes and smokeless tobacco such as chewing tobacco, snuff and dip all increase risk. The more you use, the greater the risk.
- Alcohol. Moderate to heavy drinking raises the risk. Smoking and drinking together multiply it: the American Cancer Society says people who both drink and smoke heavily have a risk about 30 times higher than people who do neither.
- Betel quid, areca nut and gutka. Chewing these, common in South and Southeast Asia, increases the risk of mouth cancer.
- HPV infection. Certain types of HPV, mainly HPV16, cause most cancers of the oropharynx, which includes the base of the tongue. HPV is found much less often in cancers of the front of the tongue.
- Age and sex. Risk rises with age, and men are about twice as likely as women to develop mouth and throat cancers.
- Long-term tongue inflammation. Ongoing conditions such as glossitis (an inflamed tongue) have been linked to a higher risk of tongue cancer.
- A diet low in fruit and vegetables. Several studies link this to higher risk.
- Rare inherited conditions, such as Fanconi anaemia and dyskeratosis congenita.
Some suggested risks remain unproven, including mouthwash with a high alcohol content, ill-fitting dentures and poor oral health. Researchers are still studying them.
Having a risk factor does not mean you will get tongue cancer, and some people who get it have no known risk factors.
How is tongue cancer diagnosed?
Diagnosis usually follows these steps:
- Examination. A GP or dentist asks about your symptoms and lifestyle, then looks and feels inside your mouth and around your neck and jaw.
- Referral. If something needs a closer look, you may be referred urgently to a specialist, such as an oral and maxillofacial surgeon or an ear, nose and throat (ENT) team. An urgent referral does not mean you have cancer.
- Biopsy. A small piece of tissue is removed, usually under local anaesthetic, and examined under a microscope. This is the only way to confirm cancer.
- Scans. If cancer is found, scans such as CT, MRI, ultrasound or PET-CT show its size and whether it has spread.
- HPV testing. Base of tongue cancers are usually tested for HPV, as this affects treatment and outlook.
The results are used to give the cancer a stage, from I (small and contained) to IV (larger or spread further). Staging guides treatment.
Tongue cancer treatment
Treatment depends on where the cancer is, its size and stage, your general health and your own preferences. A team of specialists, often called a multidisciplinary team, plans it with you.
Surgery
Surgery is the main treatment for cancer at the front of the tongue. The surgeon removes the tumour along with a margin of healthy tissue. This is called a glossectomy. Most people need a partial glossectomy, where only part of the tongue is removed. Larger cancers may need more extensive surgery.
The surgeon may also remove lymph nodes from the neck (a neck dissection) to check whether the cancer has spread. If a large area is removed, it can be rebuilt using tissue from elsewhere in the body, often the forearm or thigh, to help with speech and swallowing.
Radiotherapy
Radiotherapy uses high-energy radiation to destroy cancer cells. It may be given after surgery when there is a high chance of the cancer coming back, or as the main treatment when surgery isn’t suitable. It is also a common treatment for base of tongue cancers. Most people have external beam radiotherapy. In some cases, radioactive material is placed inside or near the tumour, which is called brachytherapy.
Chemotherapy
Chemotherapy uses medicines to kill cancer cells. For tongue cancer it is most often given alongside radiotherapy (chemoradiation) to make the radiotherapy work better. It is also used when cancer has spread to other parts of the body.
Targeted therapy
Targeted drugs act on specific features of cancer cells. Cetuximab blocks a protein called EGFR that helps some cancer cells grow. It is mainly used for advanced cancer or cancer that has come back.
Immunotherapy
Immunotherapy helps your immune system find and attack cancer cells. Drugs called PD-1 inhibitors, such as pembrolizumab and nivolumab, are used when tongue cancer has come back or spread. For some larger oral cavity cancers, current American Cancer Society guidance says a checkpoint inhibitor may also be given before and after surgery. Not everyone is suitable, and availability varies by country.
Treatment at a glance
This summary describes cancers of the front of the tongue. Base of tongue cancers are often treated differently.
|
Stage |
Usual approach |
|
Early (stages I–II) |
Surgery, often with a neck dissection. Radiotherapy alone if surgery isn’t suitable. Radiotherapy or chemoradiation after surgery if the risk of return is high. |
|
Locally advanced (stages III–IVA) |
Surgery and neck dissection, often followed by radiotherapy or chemoradiation. Immunotherapy before and after surgery may be offered. |
|
Spread or returned (stages IVB–IVC, recurrent) |
Chemotherapy, cetuximab, immunotherapy or a combination. Radiotherapy can relieve symptoms. Clinical trials may be an option. |
Recovery and rehabilitation
Treatment can affect speech, swallowing, taste and saliva. Speech and language therapists help people relearn speaking and swallowing, and dietitians help with eating well during recovery. Your dentist and cancer team will also want to keep a close eye on your mouth, as radiotherapy can affect your teeth and gums.
Can tongue cancer be cured?
Many tongue cancers can be treated successfully, especially when found early. The outlook depends mainly on how far the cancer has spread when it is diagnosed.
The figures below are 5-year relative survival rates from the US SEER programme for people diagnosed between 2016 and 2022. Relative survival compares people with tongue cancer with people of the same age who don’t have it.
|
Stage at diagnosis |
Share of cases |
5-year relative survival |
|
Localised (only in the tongue) |
28% |
88.2% |
|
Regional (spread to nearby lymph nodes) |
58% |
69.9% |
|
Distant (spread to other organs) |
10% |
38.4% |
|
All stages combined |
71.4% |
These numbers are averages from large groups of people. They cannot predict what will happen to one person, and outcomes may differ outside the US. HPV-positive base of tongue cancers generally respond better to treatment than HPV-negative ones, although this advantage is smaller in people who smoke. Your own specialist is the best person to explain your outlook.
How to lower your risk of tongue cancer
Not every tongue cancer can be prevented, but these steps lower the risk:
- Don’t use tobacco in any form. Quitting greatly lowers your risk, even after many years.
- Limit alcohol, and especially avoid drinking and smoking together.
- Avoid betel quid, areca nut, gutka and paan masala.
- Consider the HPV vaccine. It works best before someone becomes sexually active, and some adults can also have it. Ask your doctor whether you are eligible.
- Eat plenty of vegetables and whole fruit. Our guide to the foods your body needs to lower disease risk covers how to build that kind of diet.
- Keep up regular dental check-ups. Dentists look at the soft tissues of your mouth, not just your teeth. Have sharp teeth and badly fitting dentures fixed.
- Check your mouth yourself and act on anything that lasts more than 3 weeks.

Don’t ignore a sore that won’t heal
Most tongue problems turn out to be harmless. The few that aren’t are far easier to treat when they are found early. If an ulcer, patch, lump or pain on your tongue lasts more than 3 weeks, book an appointment with your dentist or GP rather than waiting for it to go away.
For more practical guides, browse our health articles.





